The Hair Transplant Procedure
We Set the Standard Ten Years Ago and Then Reinvented It
Ten years ago we set a new standard for the hair transplant procedure. We have not stopped reinventing the process since, and almost every step is different now. We changed how we design hairlines, extract hair, and insert it. We’ve also developed ways to prep procedures, preserve grafts, and promote graft survival after surgery for greater yield.
Results are more natural now. We achieve more coverage and greater density. We can conceal procedures better and get you back to normal activity sooner.
Some patients wonder if procedures are actually different between clinics. We answer that we have drastically different ways of performing procedures in our own clinic. Our basic procedure sets a standard for the industry. Our most refined procedure? It is likely something you never thought was possible. Contact Northwestern Hair Restoration today for more information.
Before
After
Two Procedures, Ten Years Apart
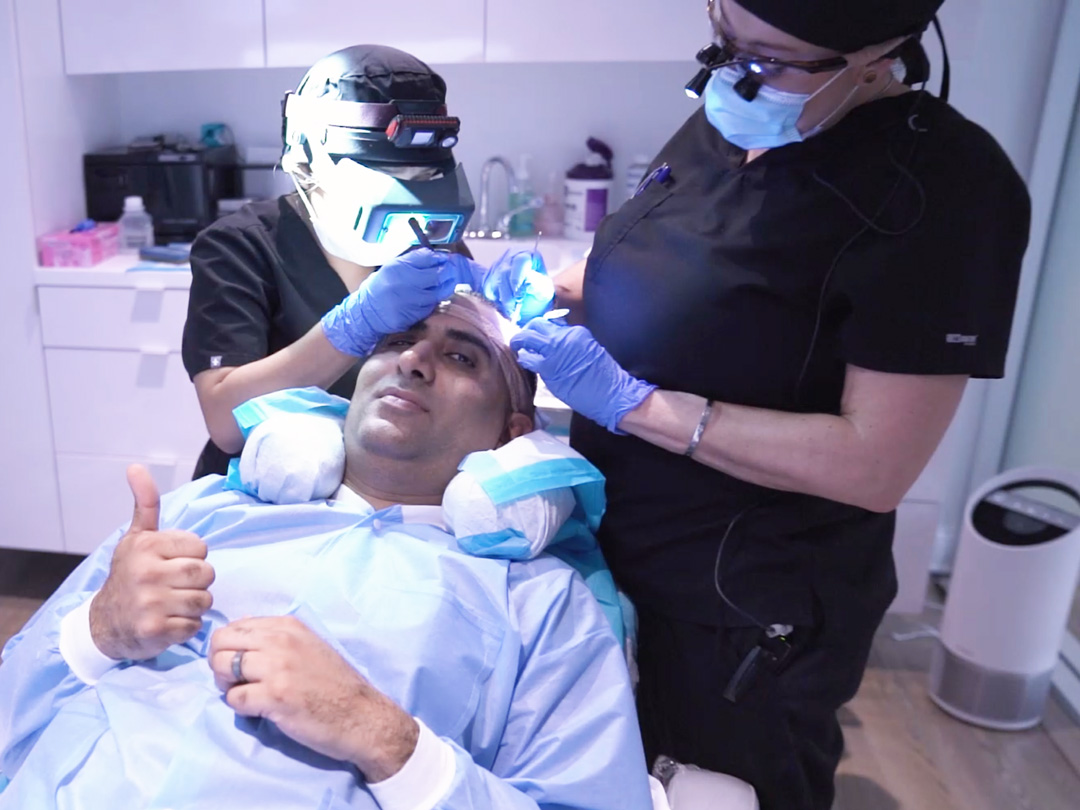
Below are two procedures, filmed ten years apart. The procedures couldn’t be any different. The first procedure was on myself. This is when I became the patient and my greatest critic. The second procedure is how we can perform transplants today at Northwestern Hair Restoration. It’s a must-see. Record-setting graphs for coverage and density. Immediate results. Totally undetectable, back to physical work in two days. Simply amazing.
Ten Years Ago: Dr. Rawlani's Own Procedure
I had two hair transplants. This was my first. I wanted to work on my own hairline, and I wanted to know exactly what I was asking patients to go through. Although this procedure sets the standard for the industry, it was poorly planned and executed. It showed me that I had much to improve.
Before
After
2026: The Current Procedure
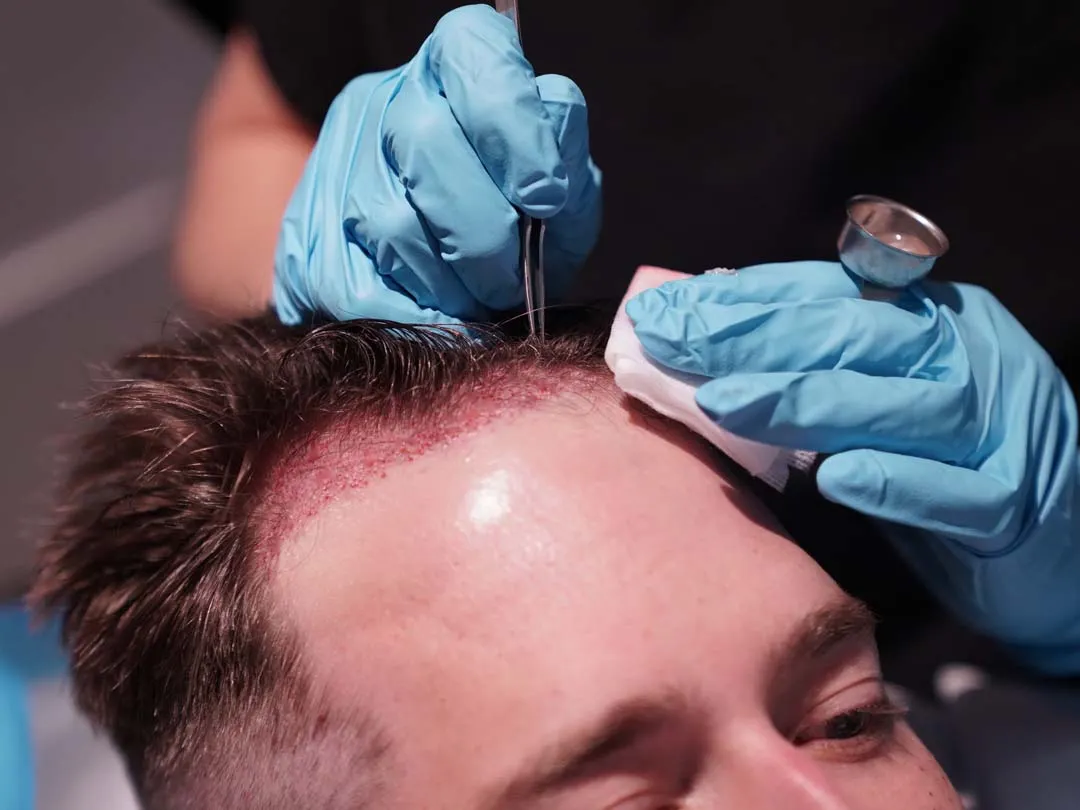
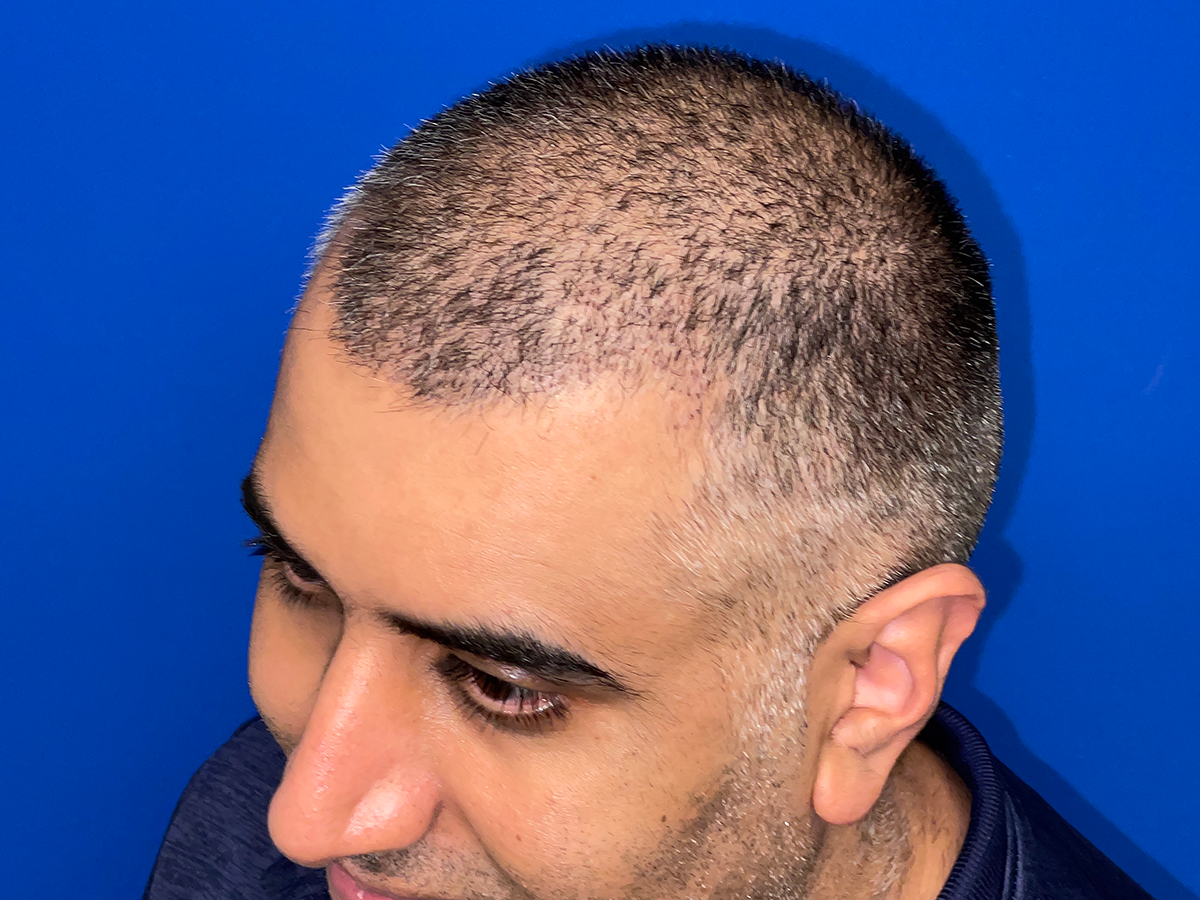
This was our most recent procedure before creating this web page. Over 4,000 grafts were performed using four different hair transplant techniques we developed in-house. The results were immediate. The procedure was completely undetectable, and the patient was back to physically demanding work in two days.
Static, standardized process for everyone. Limited to the hairline
Dynamic designs for the hairline and crown that evolve timelessly as you age
Naturalness
Dependent on body's healing and scarring
Influenced by techniques such as Micro PUE® extraction
Ten years ago, we performed one procedure a day. Now, we perform one procedure every other day. The time between procedures allows us to plan for complex procedures or innovate upon techniques. The day between procedures is also what makes the rest of it possible: one-on-one consultation time, one-on-one aftercare, and direct contact with me throughout your entire healing.
Raises the question of how many grafts can be taken in a day and leaves the donor area intact. Full detail on its own page.
GRAFT YIELD
ACS pre-procedure
Increases blood supply and growth factors in the recipient area before grafts are placed.
Plasmonic preservation
Grafts are held in your own plasma.
Iso-hypothermal preservation
Holds the grafts at a constant cold temperature. Cold is easy; constant is the hard part. Temperature that drifts up and down puts follicles through freeze-thaw cycles, forms ice crystals, and damages them.
High-volume local anesthesia
The volume separates the hairs, so they come apart with less cutting. This protects the follicles next to the one being taken. Described in full in the pain section.
ACS post-procedure
Supports blood flow and metabolism through the first weeks after placement. See below.
DENSITY AND PLACEMENT
Intrafollicular placement
Places grafts between existing follicles, so density can be built in areas that still have native hair.
SP89 blades
Allow placement at high density along the hairline. This is what produces a hairline that feathers instead of stopping in a line.
CONCEALMENT
Discreet PUE®
Extraction pattern that leaves the donor area unreadable.
Low Tapered Fade
Haircut technique, performed in-house, that hides the donor area.
Roman Hair Shade
Haircut technique, performed in-house. Used alone, it concealed a 6,119-graft session.
IMMEDIATE RESULT
Long Hair PUE®
Transplants the hair at length, so you see the result the same day instead of waiting out the growth phase. The transplanted hairs still shed on the normal schedule — day one shows you the design, not the final result.
What We Added Before the Procedure
Timeless Hairline Design & Crown Design
The hairline and crown are designed against how your hair loss will progress, not against how your head looks today. A hairline that suits a thirty-two-year-old face and fails a fifty-year-old one is a bad design.
Pre-Procedure ACS
Not every case includes one. We use it when there has been a previous hair transplant, previous surgery on the scalp, or a mature high-density hairline, among other reasons. It increases blood supply and builds up growth factors in the area before any grafts go in. It also tells us how that specific scalp takes anesthesia. We have already numbed it once and watched what happened. On the day of surgery, the first dose is not an estimate.
What We Added After the Procedure
Post-Procedure ACS
A newly placed graft needs new blood vessels. The body builds those vessels in response to the graft’s metabolic demand. But meeting that demand requires blood vessels that do not yet exist. The graft is asking the body for the thing it needs in order to survive long enough to get it. Post-procedure ACS supports the graft through that gap.
Maintenance Therapy (Northwestern Access)
Maintenance therapy is shipped to your home. The result you paid for depends on what happens over the following months, not just on the day of surgery.
Aftercare
The aftercare videos are the same ones we filmed a decade ago. Healing has only gotten easier, and the instructions were detailed enough the first time that patients who watch them stop calling us.
THE PROCEDURE DAY, STEP BY STEP
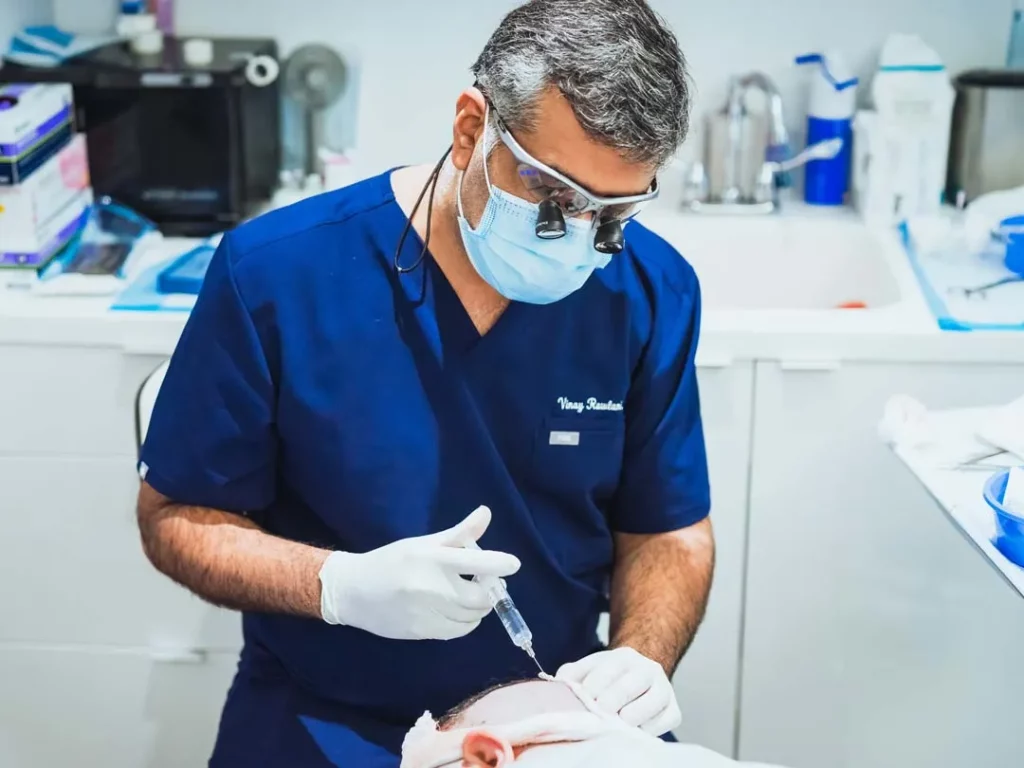
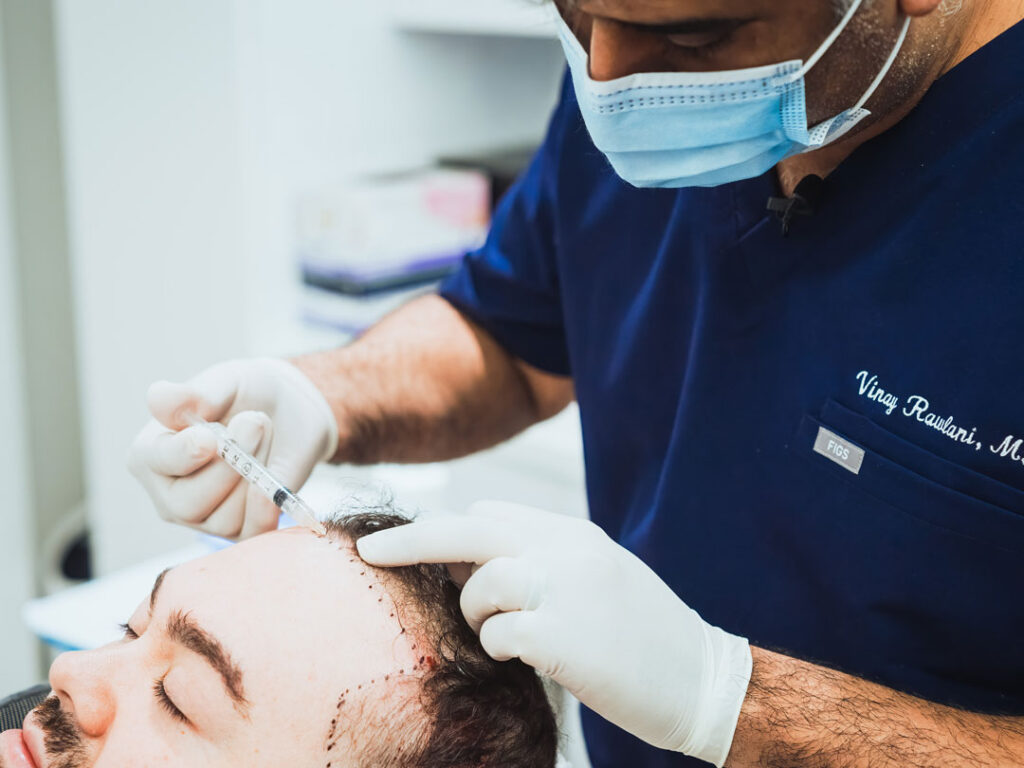
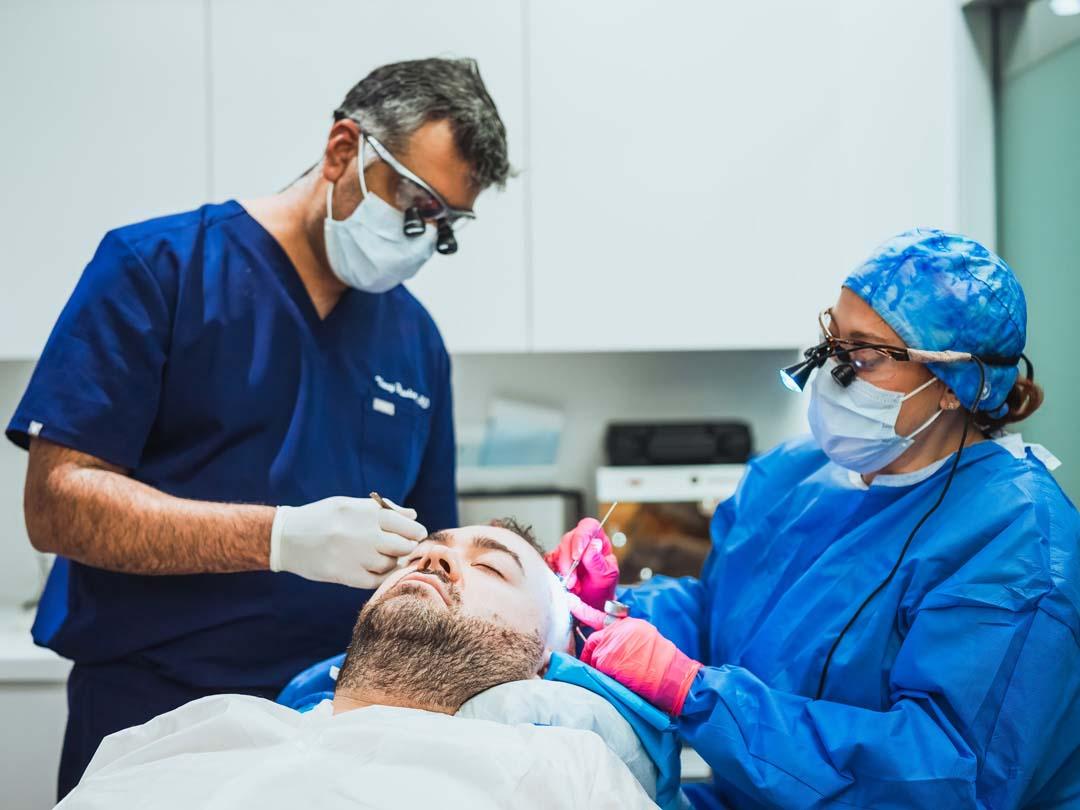
One procedure, one day. Dr. Rawlani, Lyda, and Deliaa are on your case from the first graft out to the last graft in.
You will arrive at 6:30 am at 3 East Huron Street, Chicago. Wear a button-up shirt and comfortable clothes. Bring the prescriptions we sent you. You don’t need anything else. We provide you with everything you need for aftercare.
Review your goals
You meet the team, and we go through what you want.
1
2
Design
The hairline or crown design is agreed on your head, in a mirror. Nothing is placed until you have seen it and approved it.
3
Haircut
Our barber cuts your hair. On concealed cases this is the Low Tapered Fade or the Roman Hair Shade, and it is part of how the procedure is hidden.
Numbing
We numb the donor area. This is the part patients report as briefly uncomfortable for about five minutes, with the typical pain score being 3 to 4 out of 10.
4
5
Extraction
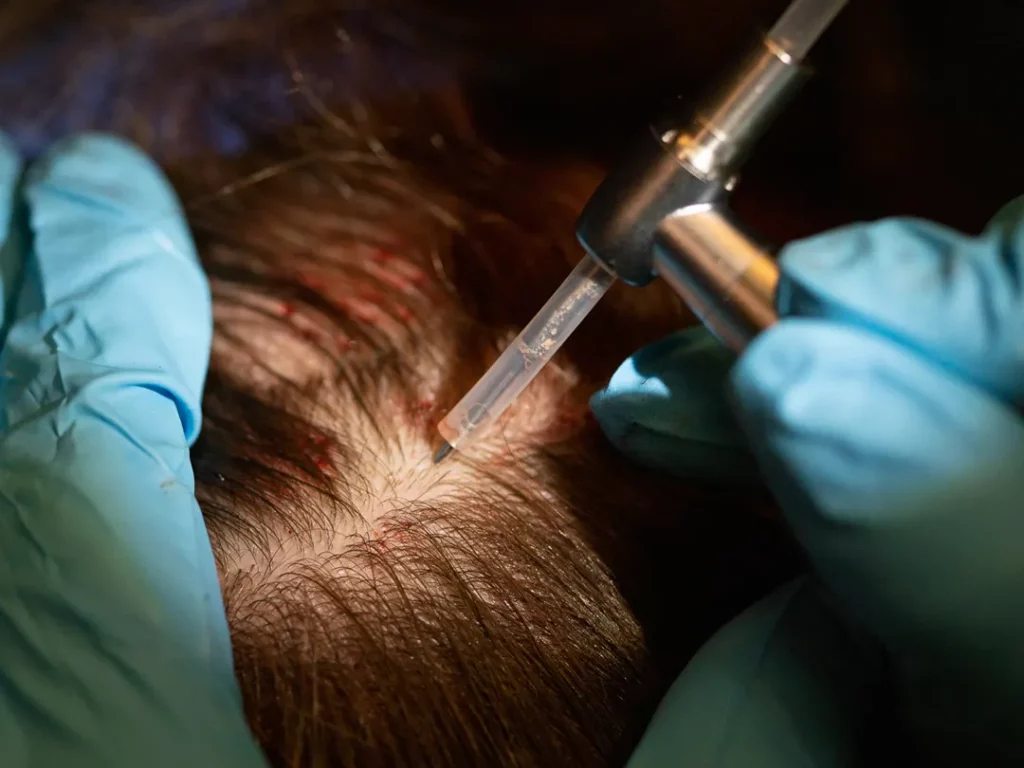
You lie on your stomach. We take the grafts individually. It takes two to four hours, depending on the number.
Graft evaluation
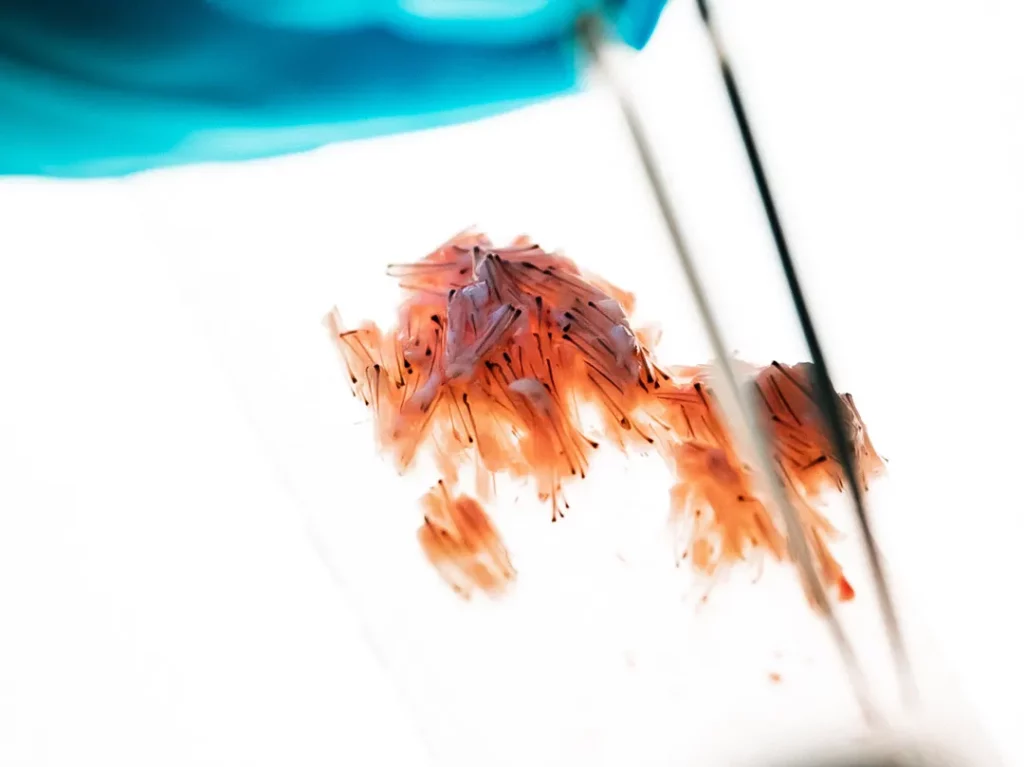
Every graft is checked and processed as it comes out.
6
7
Lunch
Ordered from a restaurant you pick.
Numbing again
We numb the placement area before any grafts go in.
8
Placement
The grafts go in, at the density and direction set by the design.
9
You Will Not Be Driving Home
If you take the benzodiazepine — over 95% of patients do — you cannot drive. It is active for about four hours, and we aim to have you clear of it before you leave, but it stays in your system for 24 hours. That is our rule, not a comment on how you will feel. The other 5% skip the medication, and driving themselves is usually why.
Pain: How We Control It
Patients report 3 to 4 out of 10, for about five minutes in the morning and two minutes in the afternoon. The rest of the day, zero. After surgery, 98% report no pain at all. Here is how that works.
The Benzodiazepine
Diazepam (Valium), taken by mouth. No IV. It handles anxiety, and how much you get is your choice:
None. Some patients would rather be fully awake, and patients who have done this before often know they do not need it.
Enough that the anxiety goes away. Most patients.
Enough to sleep through the morning, or through the whole day if you would rather use the time that way.
It matters most in the first thirty minutes. After that most patients have seen how the day runs and settle down on their own.
The Local Anesthesia
While Benzodiazepine controls anxiety to your comfort, the local anesthesia blocks all sensation and is dosed specifically to your scalp.
High concentration
Blocks targeted areas in 30 to 40 seconds and is great for touch ups.
High volume, lower concentration
Lasts several hours in the scalp. The fluid also separates the hairs, which makes extraction easier and protects the follicles next to the one being taken.
Scalps differ. Older scalps often have looser connective tissue and take more volume of anesthesia. Some patients clear anesthetic quickly and need specific areas re-dosed. We choose the concentration and the volume for your scalp in particular.
Where This Came From
During my plastic surgery training at Northwestern, Dr. Thomas Mustoe and Dr. Neil Fine were developing conscious sedation — operations that would normally require a hospital operating room and general anesthesia- performed in the office instead, using anti-anxiety medication and local anesthesia together. Patients recovered faster and got back to normal life sooner. They are still my mentors. I used conscious sedation on the first hair transplant I performed, and it worked beautifully. I never knew that pain was an issue during transplantation because we never experienced it, thanks to the work of Dr. Mustoe and Dr. Fine that preceded me. However, I have refined this method specifically for hair patients. It only requires expertise in two medications.
If You Have Had a Transplant Before
A previous hair transplant leaves scar tissue around the old donor site, and sometimes in the recipient area. Scar tissue can stop anesthetic from reaching the nerve. Revision cases need higher concentrations, placed differently, because the tissue does not behave like untouched scalp. This is also where a pre-procedure ACS session is most useful. We have already numbed that scalp once and know how it responds.
What Happens in the Afternoon
The top of the scalp has better blood flow than the back, so it clears anesthetic faster. Patients who have felt nothing all morning expect the same in the afternoon. This is the one point in the day when sensation comes back. When you feel us working in an area, that tells us two things: the anesthesia is wearing down, and exactly where. It also tells us we have about thirty minutes left on that dose. We re-dose, and you are numb again in about ten minutes. Watching for this is one of my jobs during the procedure, alongside the surgery. There should be no pain. Any sensation means we act, and we would rather act early. How your scalp handled the first dose also tells us what the touch-up should be.
After Surgery
Pain after surgery
98% of patients report none. The exception tends to be young men.
Pain medication
Usually off it by noon the next day and on just Tylenol after






 EXTRACTION
 GRAFT YIELD
 DENSITY AND PLACEMENT
 CONCEALMENT
 IMMEDIATE RESULT